
Cholesteatoma · What It Is, Causes, Signs, Symptoms, Diagnosis, and More

Published: Aug 27, 2026
Author: Georgina Tiarks, MD•
Editor: Alyssa Haag, MD•
Editor: Józia McGowan, DO•
Editor: Kelsey LaFayette, DNP, ARNP, FNP-C•
Editor: Lily Guo, MD•
Editor: Arianna Succi, MD
Illustrator: Abbey Richard, MSc
7-day free trial

Go deeper with Osmosis

Osmosis is a learning platform with videos, questions, and AI tools to help you master topics like this.

4.8 · 12,000+ reviews
Watch quick, visual videos
Practice with Qbank-style questions
Use AI to explain, quiz, and review
Study anytime with the mobile app
Try Osmosis Free

No credit card required

What is a cholesteatoma?

A cholesteatoma is a benign, locally invasive mass composed of keratinizing squamous epithelium that grows in the middle ear. Keratinized squamous epithelium is a type of tissue composed of layers of flat (squamous) cells and a superficial layer of dead, keratin-rich cells. Keratin is a protein that helps form hair, skin, and nails. Cholesteatomas may be congenital or acquired. Congenital cholesteatomas are more common in young children, whereas acquired forms can occur across a wider age range and are most common in adults in their 50s and 60s.

Cholesteatomas are essentially formed by a buildup of skin tissue and inflammatory cells. More specifically, cholesteatomas are composed of several layers, including a cystic component, matrix, and perimatrix. The cystic component forms the bulk of the lesion consists of accumulated keratin squames; it may also contain pus and debris if infected. The matrix is composed of keratinizing stratified squamous epithelium, which produces the keratin filling the cyst. The perimatrix, the outermost layer, contains inflammatory cells such as lymphocytes, neutrophils, plasma cells, histiocytes, and fibrocytes.

Learn deeper with Osmosis

Master this topic faster with videos, questions, and AI.

Used by 8M+ healthcare learners.

Try Osmosis Free

No credit card required

What causes a cholesteatoma?

The causes of cholesteatoma vary depending on whether it is congenital or acquired. Congenital cholesteatomas develop when embryologic remnants of keratinized squamous epithelium become trapped behind the tympanic membrane (i.e., ear drum). The middle ear is typically lined by simple cuboidal mucosal epithelium, which does not normally produce keratin. Keratin debris from the ectopic squamous epithelium can accumulate and form the cholesteatoma, a white keratinous mass located behind the tympanic membrane (i.e., ear drum).

The cause of primary acquired cholesteatoma is largely unknown. However, four theories have been proposed. The most accepted theory states that a pocket can form on the pars flaccida (i.e., flaccid, triangular part) of the tympanic membrane, allowing debris to accumulate. The second theory states cholesteatomas may be caused by squamous metaplasia in the middle ear, in which the normal cuboidal epithelium transforms into keratinizing squamous epithelium. The third proposes a migration of keratinized squamous epithelium from the ear canal, where it is normally found, to the middle ear through a perforated tympanic membrane. The final theory hypothesizes that hyperplasia of basal cells (i.e., cells found at the bottom of the epidermis responsible for generating new cells) in the tympanic membrane leads to their protrusion into the middle ear, allowing for excess skin cell production. 

Secondary acquired cholesteatomas can be caused by trauma, ear infection (e.g., chronic otitis media), or surgical damage causing a perforation of the tympanic membrane and allowing migration of squamous epithelium from the external ear canal into the middle ear cavity.

What are the signs and symptoms of a cholesteatoma?

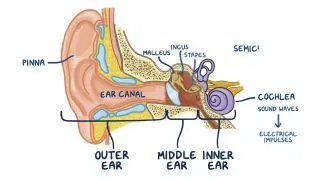
The signs and symptoms of cholesteatomas depend on the severity and location. Initially, a person may experience otorrhea (i.e., ear drainage) with or without pain (otalgia) and ear fullness. Congenital cholesteatomas may manifest in infancy with poor hearing due to ossicular chain involvement (e.g., erosion of the small middle ear bones: the malleus, incus, and stapes). Dizziness can occur if the semicircular canal (i.e., a structure in the internal ear responsible for balance) is compressed. Facial paralysis may also occur if the facial nerve, responsible for facial movements, is compressed. A cholesteatoma infection may result in foul-smelling discharge from the external ear.

Intratemporal complications of cholesteatoma (i.e., complications resulting from local destruction within the temporal bone) include labyrinthine fistulas (i.e., abnormal openings in the labyrinth of the inner ear) and permanent hearing loss. In severe cases, cholesteatomas can cause temporal bone erosion and extend into the cranial cavity, potentially causing extratemporal complications (i.e., outside of the temporal bone) such as meningitis (i.e., inflammation of the meninges) and brain abscesses.

How is a cholesteatoma diagnosed?

Cholesteatomas may be diagnosed with a thorough physical examination by a healthcare professional. A complete physical exam of the head, neck, cranial nerves, and ear may be necessary. The cholesteatoma may appear as a white, keratinous mass on otoscopic examination. An audiogram, Weber, or Rinne tests may also determine the presence of associated hearing loss, along with its severity and type. An audiogram measures the range of frequencies and intensities that an individual can hear, while Weber and Rinne tests can assess whether the hearing loss is sensorineural (i.e., inner ear damage) or conductive (i.e., outer ear damage). These tests can also determine which ear is affected.

If intracranial complications are suspected, a brain computed tomography scan (CT scan) or magnetic resonance imaging (MRI) may be required to investigate the possibility of bone erosion, brain abscesses, or a labyrinthine fistula.

How is a cholesteatoma treated?

Treatment of a cholesteatoma depends on the size, surgical candidacy, and symptoms. Surgery is the only curative treatment. A CT scan is typically performed beforehand to assess the extent of the disease and aid in surgical planning. Surgical removal can be achieved through mastoidectomy (i.e., removal of mastoid bone to access middle ear space) or tympanoplasty. Surgical removal can prevent further complications from compression and infection. Nonetheless, cholesteatomas may recur even after surgical removal.

An infected cholesteatoma can be challenging to treat without completely removing the cholesteatoma. Systemic antibiotics are usually ineffective as there is no blood supply to the keratin mass, while topical antibiotics often do not penetrate deep enough into the mass to completely resolve the infection. Therefore, surgical removal is the best option to remove the source of infection.

Even after cholesteatoma surgery, hearing loss may persist, although reconstructive surgeries – such as myringoplasty or tympanoplasty – may be able to improve hearing.

What are the most important facts to know about cholesteatomas?

Cholesteatomas are middle ear masses that develop from accumulated skin cell debris consisting of keratinized squamous epithelium, necrotic debris, and inflammatory cells. Cholesteatomas may be congenital or acquired. Individuals with cholesteatomas may experience otorrhea, conductive hearing loss, dizziness, and facial nerve palsy. Brain abscesses, meningitis, and labyrinthine fistulas may develop from bone erosion, in severe cases. A complete physical examination of the head, neck, and ear is required to make a diagnosis. Treatment relies primarily on surgical removal of the cholesteatoma.

Key Takeaways

Definition 

Benign, locally invasive mass of the middle ear, consisting of keratinizing squamous epithelium and keratin debris 

Types  

- Congenital (children)  

- Acquired  

Structure 

- Inner cystic component (keratin squames +/– pus and debris)  

- Matrix (keratinized squamous epithelium) 

- Perimatrix (inflammatory cells)  

Causes 

- Congenital cholesteatoma: embryologic remnants of keratinized squamous epithelium behind an intact tympanic membrane 

- Primary acquired cholesteatoma: 4 hypotheses 

- Retraction pocket in the tympanic membrane 

- Squamous metaplasia  

- Basal cell hyperplasia from the tympanic membrane  

- Migration of keratinized squamous epithelium from ear canal 

- Basal cell hyperplasia in tympanic membrane 

- Secondary acquired cholesteatoma: tympanic membrane perforation (trauma, infection, surgery) 

Signs and Symptoms 

Otorrhea  

- Conductive hearing loss 

- Ear fullness 

- Otalgia (pain) 

-Dizziness  

- Facial nerve palsy  

- Complications:  

- Intratemporal: labyrinthine fistulas, permanent hearing loss  

- Extratemporal: meningitis, brain abscesses 

Diagnosis 

- Physical examination  

- Otoscopic examination  

- Hearing assessment:  

- Audiogram  

- Weber and Rinne tests  

- Suspected intracranial complications: imaging (CT scan, MRI)  

Treatment 

- Surgical excision (tympanoplasty and mastoidectomy) 

- Hearing reconstructive surgery  

Students say Osmosis is 100% worth it

Because Osmosis saves them time. Lowers stress. And actually helps them remember when it counts.

I used Osmosis to prepare for my first medical school licensing exam! Super helpful and interactive for people who may not do great with just pages of text info!"

Cecilia Ruiz

Cecilia Ruiz

MD student

Sayan Misra

I have used Osmosis for about four years. Best thing I have ever used for my medical studies."

Sayan Misra

Sayan Misra

Med student

Osmosis videos are superior because they define simple concepts, tell a story with a clear progression, and provide context."

Jay Pate

Jay Pate

Dental student

References


Kuo CL, Shiao AS, Yung M, et al. Updates and knowledge gaps in cholesteatoma research. Biomed Res Int. 2015;2015:854024. doi:https://doi.org/10.1155/2015/854024 


Liu D, Zhang H, Ma X, Dong Y. Research progress on non-coding RNAs in cholesteatoma of the middle ear. Clin Exp Otorhinolaryngol. 2023;16(2):99-114. doi:https://doi.org/10.21053/ceo.2022.01319 


Popescu C, Văruț RM, Puticiu M, Belghiru VI, Banicioiu M, Rotaru LT, et al. Comprehensive management of cholesteatoma in otitis media: diagnostic challenges, imaging advances, and surgical outcome. J Clin Med. 2024;13(22):6791. doi:https://doi.org/10.3390/jcm13226791 


Richards E, Muzaffar J, Cho WS, Monksfield P, Irving R. Congenital mastoid cholesteatoma. J Int Adv Otol. 2022;18(4):308-314. doi:https://doi.org/10.5152/iao.2022.21450 


Xing B, Dang Y, Xi K. Cholesteatoma: an updated review of molecular pathogenesis and potential therapeutic directions. Curr Med Chem. Published online May 19, 2025. doi:https://doi.org/10.2174/0109298673404489250515074316