Complete metabolic panel (CMP) - Potassium: Nursing
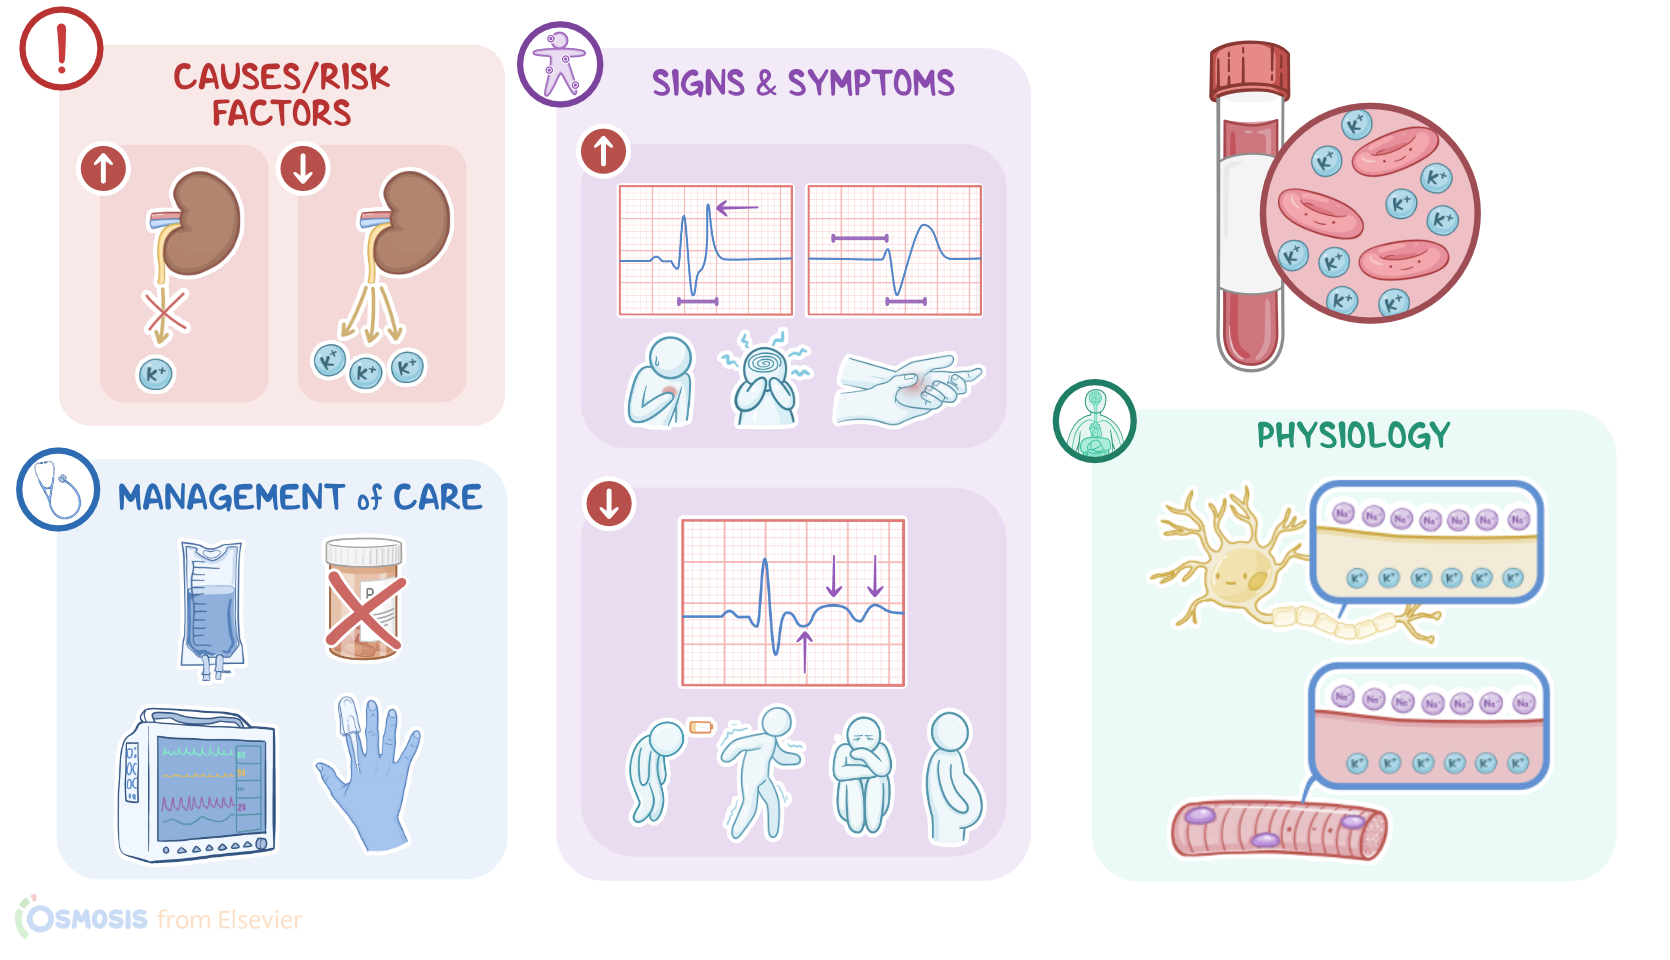
A client with a history of chronic kidney disease arrives at the emergency department via ambulance and reports feeling weak and experiencing palpitations. The electrocardiogram, or ECG, reveals peaked T waves and a prolonged QRS interval. Based on these findings, a complete metabolic panel, or CMP, is ordered to check their serum potassium level. Now, potassium, which has the symbol K+, is a positively charged ion, or cation. About 98 percent of the body’s total potassium is found in the intracellular fluid, while the remaining 2 percent is in the extracellular fluid. Potassium mostly comes from the diet, and once ingested, a tiny amount is excreted through sweat and the gastrointestinal tract, while most of the excess potassium is excreted by the kidneys.
A normal potassium concentration is essential for maintaining the overall electrochemical gradient across the membrane of each cell, which supports nervous system function, and the contraction of skeletal, smooth, and cardiac muscles. So, the plasma level of potassium can be measured on its own or as part of a CMP or a complete metabolic panel; which is also called a basic metabolic panel, or BMP. This level represents the amount of potassium in the plasma. In adults, normal potassium levels range from 3.5 to 5.1 mEq/L. Critical values are 2.5 mEq/L or less and 6.0 mEq/L or more. All right, now there are certain conditions that can alter a client’s potassium level. The three primary causes of a high potassium, or hyperkalemia, are decreased potassium excretion, increased potassium intake, and a potassium shift from inside the cells to outside the cells.
First, let’s look at decreased potassium excretion. This can occur from conditions like acute or chronic renal disease; or the use of certain medications, like potassium-sparing diuretics such as spironolactone; non-steroidal anti-inflammatory drugs, or NSAIDs, like ibuprofen; and angiotensin converting enzyme, or ACE, inhibitors, like captopril. Decreased potassium excretion can also be caused by adrenal cortex dysfunction due to disorders like Addison disease, because dysfunction of the adrenals leads to low levels of aldosterone, which results in increased sodium excretion and excess potassium retention. The next cause of hyperkalemia is from an increased intake of potassium. This can come from taking oral potassium supplements, overuse of salt substitutes, intravenous infusions of potassium, or medications that contain potassium, such as penicillin K.
| POTASSIUM | ||
| KEY POINTS | NOTES | |
| PHYSIOLOGY |
| |
| PATHOLOGY |
| |
| INDICATIONS |
| |
| NURSING IMPLICATIONS |
| |
No notes for this video yet
Try adding a note below