
Prepare for the PANCE® with this emergency department scenario involving a patient experiencing generalized muscle aches, weakness and pain in the left hand. What’s the diagnosis? Let’s find out!
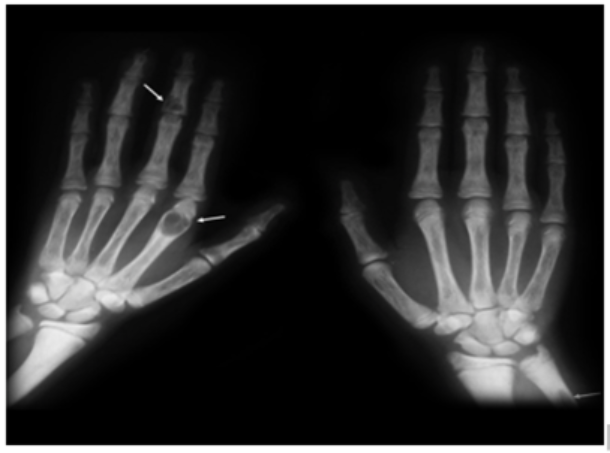
A 74-year-old woman is brought to the emergency department because of generalized muscle aching, weakness and pain in the left hand. The symptoms started gradually a few months ago and have been progressing over time. Past medical history is notable for hypertension, type 2 diabetes mellitus, and end-stage renal disease on dialysis for 2 years. Her medications include amlodipine, hydralazine, and insulin glargine. A radiograph of the patient’s hands is shown below:
Routine blood work is performed. Which of the following sets of findings will most likely be seen in this patient?
| Parathyroid Hormone | Serum Calcium | Serum Phosphate | |
| A. | Increased | Increased | Increased |
| B. | Increased | Increased | Decreased |
| C. | Increased | Decreased | Increased |
| D. | Increased | Decreased | Decreased |
| E. | Decreased | Increased | Decreased |
Scroll down to find the answer!
The correct answer to today’s PANCE® Question is…
| Parathyroid Hormone | Serum Calcium | Serum Phosphate | |
| C. | Increased | Decreased | Increased |
Correct: See Main Explanation.
Incorrect Answer Explanations
| Parathyroid Hormone | Serum Calcium | Serum Phosphate | |
| A. | Increased | Increased | Increased |
| Incorrect: This pattern is seen in tertiary hyperparathyroidism, which is a state of excessive PTH secretion after a long period of secondary hyperthyroidism, reflecting the development of autonomous parathyroid gland function. It is preemptive to diagnose this patient as tertiary hyperparathyroidism without checking the response to therapy. | |||
| B. | Increased | Increased | Decreased |
| Incorrect: This pattern is seen in primary hyperparathyroidism. In the majority of cases, primary hyperparathyroidism is caused by a benign adenoma of a single parathyroid gland that autonomously secretes PTH, resulting in elevated calcium and decreased phosphate levels. However, the patient’s history of end-stage kidney disease provides a more likely explanation for her clinical and radiographic findings. | |||
| D. | Increased | Decreased | Decreased |
| Incorrect: This pattern is seen in patients with vitamin D deficiency. Vitamin D is activated to calcitriol in the kidneys and markedly increases intestinal calcium and phosphate absorption. Lack of vitamin D causes a negative feedback response that increases PTH secretion from the parathyroid glands. However, the patient’s history of end-stage kidney disease provides a more likely explanation for her clinical and radiographic findings. | |||
| E. | Decreased | Increased | Decreased |
| Incorrect: Such set of findings can be seen in patients with humoral hypercalcemia of malignancy that is caused by secretion of parathyroid hormone-related peptide by malignant tumor cells. The rise in calcium and decline in phosphate levels cause negative feedback inhibition of endogenous PTH production, resulting in low PTH levels. | |||
Main Explanation
This patient with end-stage renal disease (ESRD) on hemodialysis has progressive bone pain, muscle weakness, and characteristic hand radiograph findings showing subperiosteal bone resorption and multiple lytic expansile lesions (i.e. brown tumors (arrows)), consistent with osteitis fibrosa cystica due to secondary hyperparathyroidism.
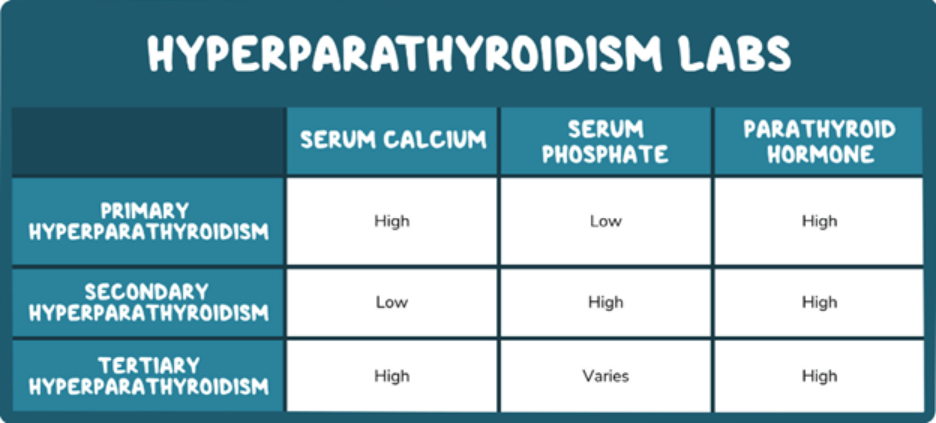
Secondary hyperparathyroidism commonly develops in patients with chronic kidney disease due to decreased renal synthesis of 1,25-dihydroxyvitamin D (calcitriol, active form). Reduced calcitriol production decreases intestinal calcium absorption, leading to hypocalcemia and stimulation of parathyroid hormone (PTH) secretion. In addition, phosphate retention in chronic kidney disease causes hyperphosphatemia, which further stimulates PTH secretion.
Osteitis fibrosa cystica is a skeletal disorder caused by chronic elevation of PTH, leading to increased osteoclastic bone resorption, bone pain, fractures, and brown tumors. (as seen in this patient).
Major Takeaway
Secondary hyperparathyroidism commonly occurs in patients with chronic kidney disease and is characterized by elevated PTH, low serum calcium, and elevated serum phosphate. Chronic PTH excess can lead to osteitis fibrosa cystica.
Want to learn more about this topic?
Review this Osmosis content: Hyperparathyroidism: Clinical sciences
References
- Bilezikian, J.P., Bandeira, L., Khan, A., Cusano, N.E. (2018) Hyperparathyroidism. Lancet. 391(10116), 168-178. Doi: 10.1016/S0140-6736(17)31430-7.
- Lofrese, J.J., Basit, H., Lappin, S.L. (2019) Physiology, Parathyroid. StatPearls [Internet]. Web Address: https://www.ncbi.nlm.nih.gov/books/NBK482510/.
- Moschella, C. (2016) Chronic kidney disease- mineral and bone disorder: Guidelines for diagnosis, treatment, and management. Journal of the American Academy of Physician Assistants. 29(7), 21-29. Doi: 10.1097/01.JAA.0000484297.49157.9b.

Get your free trial today to discover why millions of clinicians and caregivers love learning by Osmosis.
Leave a Reply