Arrhythmias - Heart blocks: Nursing
Introduction0:00–0:44
I Arrhythmias are irregular heartbeats that occur due to any disturbance in the rate, rhythm, site of origin, or conduction of the cardiac electrical impulse, which can affect the heart's ability to effectively pump blood throughout the body.
Now, a heart block or atrioventricular block occurs when there is a delay or disturbance in the conduction of cardiac electrical impulse from the atria to the ventricles.
There are 3 types of atrioventricular block or AV block for short, 1st degree AV block, 2nd degree AV block, which is further divided into Mobitz type 1 and Mobitz type 2, and lastly, 3rd degree AV block.
Physiology0:44–2:59
The cardiac conduction system is made of specialized myocardial cells that create and transport electrical potential, which play a role in regulating heart rate and rhythm.
They possess automaticity, which is the ability to generate an impulse, excitability, or the ability to respond to stimulus by initiating stimulus, conductivity, or the ability to send that impulse, and contractility, or the ability to shorten fiber length.
Alright, now let's look at the normal electrical conduction pathway in the heart on an ECG which shows how the depolarization wave flows through the heart during each heartbeat.
The normal electrical activity of the heart starts in the sinoatrial or SA node, which is considered the pacemaker of the heart.
Then the impulse is conducted through the atria, causing depolarization and creating the P wave on an ECG. When the atrial muscle cells get depolarized, they contract, pushing blood from the atria into the ventricles.
From the atria, the impulse goes to the atrioventricular or AV node, where the impulse propagation speed slows way down.
The interval from the atrial depolarization to just before ventricular depolarization is the PR interval on an ECG. This delay allows the atria to contract while the ventricles fill with blood.
From the AV node, the impulse goes through the bundle of hiss, then to the right and left bundle branches, and finally through the Perkinji fibers, which deliver the impulse to the right and left ventricles, causing them to depolarize and is represented on the QRS complex on the ECG.
This triggers simultaneous contraction of both ventricles, pushing blood into the systemic and pulmonary circulations. Finally, the ventricles repolarize to prepare for the next cycle, which allows them to relax and fill with blood called diastole.
And on ECG, ventricular repolarization will create a T wave, while the phase between ventricular depolarization and repolarization is represented by the ST segment.
Causes and risk factors2:59–3:45
Sometimes, immediately after the T wave, there's a U wave, which represents late repolarization of the ventricles. OK, now let's look at AV blocks, which are typically caused by any kind of structural damage or fibrosis to the electrical conduction system.
This damage is strongly associated with several risk factors, particularly cardiac surgery or underlying heart conditions.
These include ischemic heart disease, previous or recent myocardial infarction, congenital heart disease, myocarditis, as well as rheumatic fever.
Other risk factors include drug toxicity, typically with digoxin, calcium channel blockers, or beta blockers. Finally, elderly clients as well as athletes are at a higher risk for developing AV blocks.
Pathology3:45–5:38
OK, the pathology of AV blocks starts when any of these factors impair the function of the electrical conduction system.
Now a first degree AV block is technically not really a block, because it's more of a delay as the cardiac electrical impulses still make it to the ventricles, but result in a delayed ventricular contraction.
On the other hand, 2nd degree AV block has two subtypes, Mobitz type 1 and Mobitz type 2. In Mobitz type one, each atrial impulse encounters a longer and longer delay until one of them does not make it through to the ventricles, and you get what's called a dropped beat.
When a signal doesn't make it from the atria to the ventricles, and if a long enough time passes, then the ventricle's pacemaker cells kick in, sort of a fail-safe mechanism called a ventricular escape beat.
Like Mobits one, the heart also drops a beat in Mobits two, except this time conduction through the AV node is all or nothing.
Either the atrial impulse goes through with no delay, or it doesn't at all. A lot of times, a ratio for the overall number of beats conducted to not conducted is given like 2:1, Mobits 2 AV block.
But it's important to remember that the dropped beats happen fairly randomly, so we can't really predict exactly when the next beat will get dropped.
Mobids too can be dangerous and may result in severe bradycardia and decreased cardiac output, and it can often progress to 3rd degree AV block.
Lastly, there is 3rd degree or complete AV block, where the signal is completely blocked when moving from the atria to the ventricles every time.
Clinical Manifestations5:38–6:12
Because the atria and the ventricles each have their own pacemakers, they now contract independent of one another, which is called AV dissociation.
So in terms of clinical manifestations, clients with a first degree AV block don't have symptoms. Those with Mobitz type 1 may not have symptoms, but occasionally feel lightheadedness, dizziness, and syncope.
In contrast, most clients with Mobitz type 2 have symptoms like fatigue, confusion, dyspnea, chest pain, and syncope, though the severity can vary from client to client.
Diagnosis6:12–7:31
In 3rd degree AV block, symptoms become more severe and without treatment may lead to cardiac arrest and even death. The diagnosis of an AV block starts with the client's history and physical assessment, followed by a 12 lead electrocardiogram.
In first degree AV block, the PR interval is greater than 200 milliseconds. In Mobit's type 1 AV block, also called Weckenbach block, the PR interval gets progressively longer with each beat until a P wave is blocked completely.
So, maybe the first PR interval is 200 milliseconds, then the next is 260 milliseconds, then 300 milliseconds, and finally the next one doesn't make it to the ventricles.
In Mobit's type 2 AV block, there is no progressive prolongation of the PR interval. Instead, there are a couple of normal PR intervals followed by a dropped beat, so there are more P waves than QRS complexes.
Lastly, in 3rd degree AV block, the P waves and QRS complexes have nothing to do with each other, each appearing at their own rates.
Treatment7:31–9:00
The atrial rate is 60 to 100 BPM, whereas the ventricular rate usually ranges between 30 to 45 BPM. The QRS complex is normal if the escape rhythm starts at the bundle of hiss or above.
It is widened if the escape rhythm starts below the bundle of hiss. Now, treatment of AV block may depend on the causes, types, and severity of symptoms.
Clients with first degree AV block are typically asymptomatic and require no treatment. Now, in a symptomatic client with Mobit's type 1, 2nd degree AV block, the underlying cause of the AV block should be identified and treated when possible.
If they are hemodynamically unstable, they may benefit from atropine. If that doesn't help stabilize the client, other options include temporary cardiac pacing, beta adrenergic agonists like dopamine or dobutamine.
In clients with Mobit's type 2 2nd degree AV block that are hemodynamically stable, clients should be monitored closely for clinical manifestations of decreased cardiac output like dyspnea and chest pain due to non-conducted beats.
In unstable clients, treatments include beta adrenergic agonists and temporary cardiac pacing. Finally, in unstable clients with a 3rd degree or complete heart block, options include atropine, beta adrenergic agonists, as well as temporary pacing options.
Management of care9:00–10:22
Ultimately, implantation of a permanent pacemaker can be a solution for clients with complete heart block. All right, let's look at the nursing care you'll provide to a client with a Navy block.
Your priority goal of care is to assist with improving cardiac output. Begin by initiating continuous cardiac monitoring and assessing your client to determine if they are hemodynamically stable.
Assess their vital signs and check for symptoms of decreased cardiac output and report dizziness, decreased levels of consciousness or LOC, a heart rate less than 40 BPM, hypotension, chest pain, tachypnea, or shortness of breath to the healthcare provider.
Then administer oxygen, prepare to administer the prescribed medications, assist with cardiac pacing, and assist the healthcare team to identify the underlying cause.
OK, let's move on to client and family teaching. First, teach your client that an AV block causes a delay in the conduction of cardiac electrical impulse from the atria to the ventricles.
Review their treatment plan, including any new medications, and instruct your client to take them exactly as prescribed.
Next, talk to them about lifestyle modifications that can help keep their heart healthy. Encourage them to maintain a healthy weight and to engage in moderate physical exercise regularly as prescribed by their healthcare provider.
General client & family teaching10:22–13:25
Instruct them to eat plenty of fruits, vegetables, and whole grains, as well as lean meats and low fat or fat-free dairy products.
If they need help quitting smoking, provide them with counseling and refer them to resources for support. Then teach them how to check their pulse and BP, and instruct them to sit or lie down if they begin to feel dizzy to avoid injuries.
Now, if your client has a permanent pacemaker, let them know that the device has been implanted just beneath the skin, and that there are leads that go directly to the heart muscle.
Explain that when it senses their heart is beating too slow, it will send a signal to their heart to help it beat at the correct pace.
Review with them how to care for the incision site, and to let their healthcare provider know right away if they experience any signs of infection, including fever, redness, swelling, tenderness, or discharge at the insertion site.
Next, advise them to avoid raising their arm on the incision side above shoulder level or stretching their arm behind their back to avoid dislodging the leads and to give them a chance to become more secure inside the heart.
Also, let them know that their pacemaker could be affected by electromagnetic fields. So emphasize the importance of keeping their cell phone away from their pacemaker and review the kinds of electrical devices and medical procedures that are safe.
As well as those that could interfere with their particular type of pacemaker. Lastly, stress the importance of always carrying their pacemaker ID card with them at all times to let all healthcare providers know they have a pacemaker and to keep all of their follow-up appointments so their pacemaker can be regularly checked.
Finally, advise them to notify their healthcare provider immediately if they have a heart rate less than 60 BPM or a systolic BP less than 90 millimeters of mercury.
Stress the importance of seeking emergency medical care if they experience dizziness, chest pain, shortness of breath, confusion, or loss of consciousness.
Alright, as a quick recap, the three types of AV blocks are 1st degree AV block, 2nd degree AV block, which is further divided into Mobitz type 1 and Mobitz type 2, and 3rd degree AV block.
During the 1st degree AV block, the electrical impulse is delayed and causes a delayed ventricular contraction. A Mobitz type 1 AV block is when each atrial impulse has a longer delay until one doesn't make it to the ventricles, which causes a dropped beat.
Review13:25–15:17
On the other hand, in a Mobitz type 2 AV block, the atrial impulses either get to the ventricles without delay or not at all, and the number of conducted to non-conducted beats can occur either as a ratio or in an unpredictable pattern.
If a 3rd degree AV block occurs, the atrial impulse is completely blocked from reaching the ventricles, causing the atria and ventricles to contract independently of one another.
Clinical manifestations depend on the type of heart block and may include lightheadedness, dizziness, syncope, fatigue, confusion, dyspnea, chest pain, and without treatment, cardiac arrest, or death may occur.
Treatment isn't required for asymptomatic clients, where symptomatic clients may benefit from medications to increase their heart rate, such as atropine or beta-addrenergic agonists, temporary pacing, or a permanent pacemaker.
Nursing management is focused on improving cardiac output while closely assessing and monitoring the client and assessing for pacemaker dysfunction.
Client and family teaching includes explaining their condition, treatment plan, and medications, lifestyle modifications, pacemaker considerations, as well as symptoms to report to their healthcare provider.
| ARRHYTHMIAS - HEART BLOCKS | ||
| KEY POINTS | NOTES | |
| DEFINITION |
| |
| PHYSIOLOGY |
| |
| CAUSES AND RISK FACTORS |
| |
| PATHOPHYSIOLOGY |
| |
| SIGNS AND SYMPTOMS |
| |
| DIAGNOSIS |
| |
| TREATMENT |
| |
| MANAGEMENT OF CARE |
| |
| PATIENT AND FAMILY TEACHING |
| |
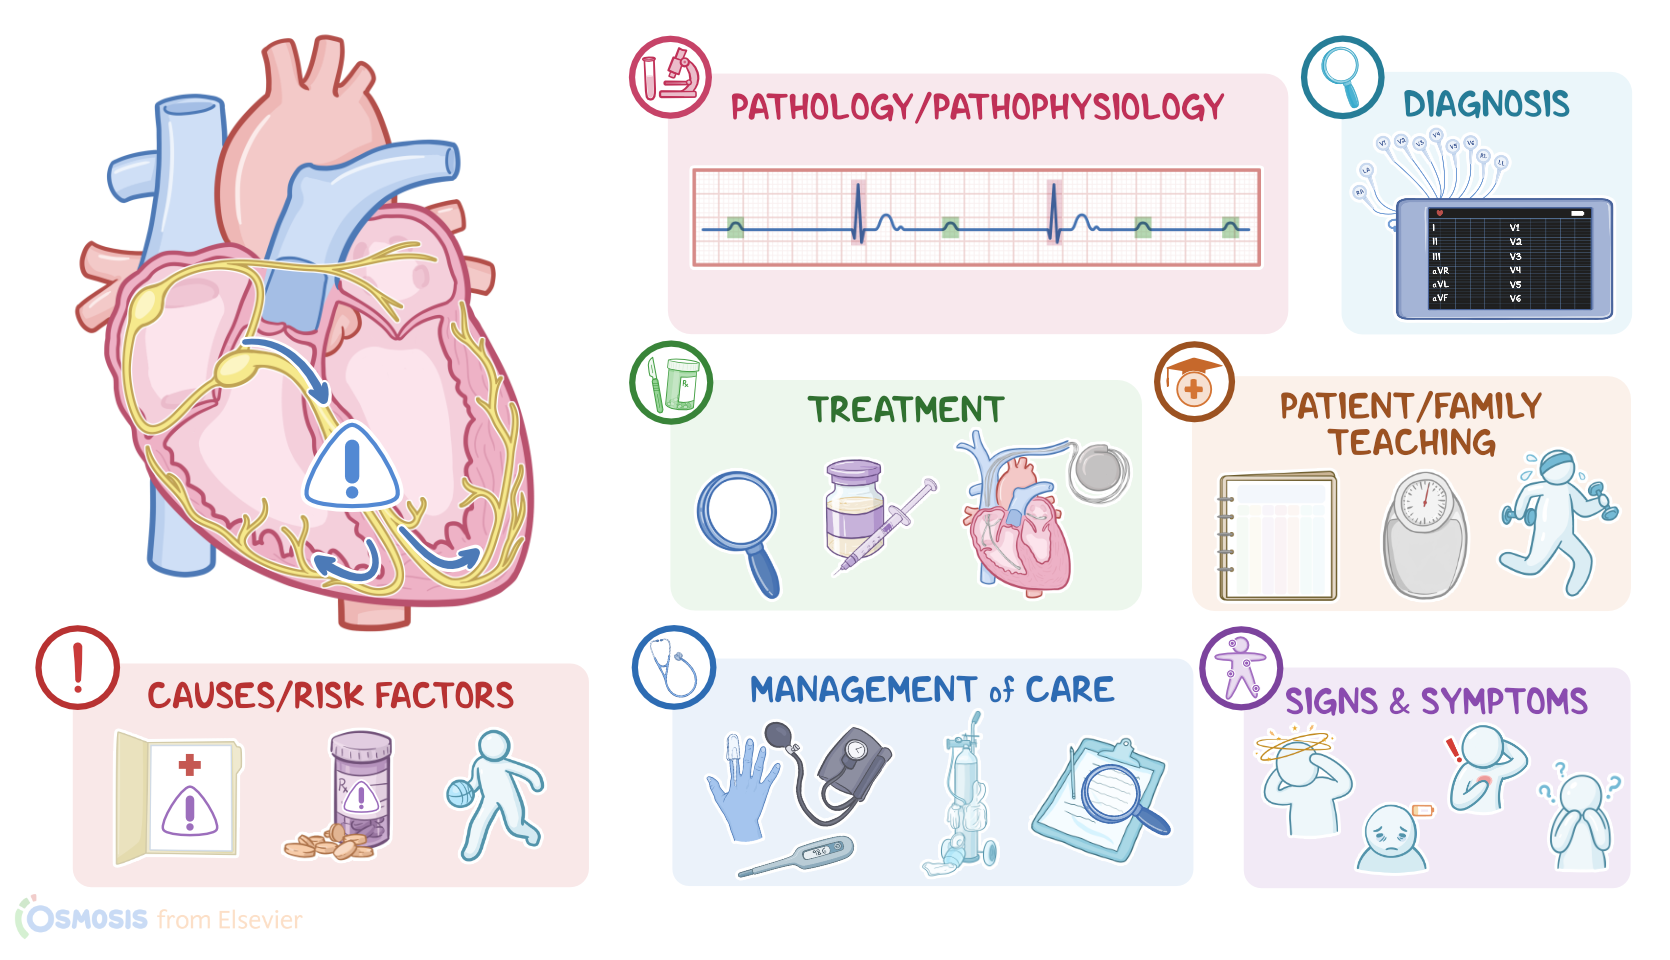
- "Critical care nursing: Diagnosis and management (10th ed.). ISBN: 978-0-443-11581-3 " Elsevier (2026)
- "Lewis’s Medical-Surgical Nursing: Assessment and Management of Clinical Problems. 12th Edition. ISBN:978-0-323-78961-5 " Elsevier (2023)
- "Medical-Surgical Nursing: Concepts for Interprofessional Collaborative Care (10th ed.). ISBN 978-0323612425" Elsevier (2020)
- "Lewis’s medical-surgical nursing: Assessment and management of clinical problems (11th ed). ISBN 978-0323551564 " Elsevier (2020)
- "Saunders comprehensive review for the NCLEX-RN examination (7th ed.). ISBN 978-0323358415 " Elsevier (2017)
- "Fundamentals of nursing (10th ed.). ISBN 978-0323810340 " Elsevier (2021)
- "Contralateral pneumothorax and pneumopericardium after dual-chamber pacemaker implantation: Mechanism, diagnosis, and treatment. 4(6), 256-259." HeartRhythm Case Reports (2018)
- "Right Bundle Branch Block: Current Considerations. 17(1), 24–30. " Current cardiology reviews (2021)
No notes for this video yet
Try adding a note below