Infertility: Nursing
Introduction0:00–0:20
Before we begin, a quick terminology update. In 2026, an international group of patient advocacy and professional organizations introduced a new name for the condition previously known as polycystic ovary syndrome or PCOS.
PCOS is transitioning to polyendocrine metabolic ovarian syndrome, or PMOS. The new name was introduced because the condition involves much more than just the ovaries and can affect body weight, metabolism, mental health, skin, and reproductive function.
Physiology0:20–2:58
The old name emphasized ovarian cysts rather than the broader endocrine and metabolic features of the condition, which may have contributed to misunderstanding, delayed diagnosis, and inadequate treatment.
As you watch the video, keep in mind that any references to PCOS refer to the condition newly named PMOS. The underlying disease process and management discussed in this video remain the same.
Infertility is defined as the inability to conceive after 12 months of regular unprotected sexual intercourse in couples of reproductive age.
Infertility can affect one or both partners, or in some cases, no cause can be found in either partner, in which case it's termed unexplained infertility.
Now, let's go over some anatomy and physiology when it comes to conceiving. The female gonads are called ovaries, which are paired reproductive organs that produce sex hormones, namely estrogen and progesterone, as well as gametes called oocytes in the process known as ooagegenesis.
These functions are an integral part of the menstrual cycle, which usually lasts around 28 days and can be divided into two phases.
First, there's the follicular phase, during which estrogen rises and the oocytes mature until ovulation, which typically occurs on day 14 of a 28 day cycle.
During ovulation, the mature oocyte is released in the fallopian tube and it can possibly be fertilized by a male gamete called a sperm.
If fertilization occurs, the fertilized egg travels down the fallopian tube and implants into the uterine lining, so pregnancy occurs.
If fertilization doesn't occur, ovulation is followed by the luteal phase, during which progesterone rises and peaks, and then hormone levels gradually decrease until menstruation occurs, and the cycle starts all over again.
The menstrual cycle is primarily controlled by two pituitary hormones, luteinizing hormone or LH for short, and follicle stimulating hormone or FSH for short.
But a normal concentration of several other hormones, including thyroid hormones, cortisol and prolactin, is needed for the menstrual cycle to unfold optimally.
On the other hand, the male gonads are called testicles or testes, which are also paired reproductive organs that lie in the scrotum.
Causes & risk factors2:58–6:31
The testes produce the sex hormone testosterone, and they're also where spermatogenesis or the development of sperm happens.
Just like oagegenesis, spermatogenesis is also controlled by LH and FSH. The difference is that spermatogenesis occurs constantly and doesn't follow a cyclical pattern.
The mature sperm are stored in the epididymis, which is a little coiled tube found on one side of the testicle. During ejaculation, sperm is released from the epididymis and travels through a series of reproductive ducts, including the vas deferens, to eventually exit the body through the urethra.
Finally, remember that sex hormones also play a role in the normal reproductive function and the development of secondary sex characteristics.
Estrogen and progesterone control menstrual cycles and enable the normal development of the female's secondary sex characteristics, such as enlargement of the breast.
Testosterone on the other hand, is needed for spermatogenesis, and the development of male secondary sex characteristics, such as facial and body hair, enlargement of the larynx, and maturation of voice.
That being said, infertility can affect one or both partners. The causes of infertility in individuals with female reproductive organs can be subdivided into two main groups.
The first group covers ovulatory dysfunction, which can result from premature ovarian failure, meaning the ovaries run out of oocytes before menopause, as well as endocrinological, genetic or developmental causes.
Endocrinological causes include polycystic ovarian syndrome or PCOS, which is a condition characterized by excess testosterone production, Cushing's syndrome or excess cortisol production, hyperprolactinemia, where a tumor in the pituitary overproduced prolactin, and hyperthyroidism or hypothyroidism.
Another cause is functional hypothalamic amenorrhea, which is when the hypothalamus doesn't stimulate pituitary production of FSH and LH enough.
This can be caused by excessive exercising, stress, or having a body mass index or BMI below 18.5 kg per square meter or over 25 kg per square meter.
Alternatively, the most common genetic or developmental causes include Turner syndrome, which is when the individual only has one X chromosome instead of 2, or Coleman syndrome, which is when the hypothalamic neurons that produce gonadotropin releasing hormone or GNRH don't develop properly.
On the other hand, the second group covers conditions that can affect the normal anatomy of the reproductive system. Such as adhesions of the fallopian tubes, uterine tumors, pelvic inflammatory disease caused by sexually transmitted infections, or other infections in the female reproductive organs, and endometriosis, which is when the lining of the uterine cavity called the endometrium grows in other places, such as the ovaries or fallopian tubes.
On the flip side, causes of infertility in individuals with male reproductive organs can be classified into three main groups.
The first group includes pre-testicular causes, such as Coleman syndrome, Prader-Villi syndrome, a genetic condition caused by a gene defect located on chromosome 15, which disrupts the function of the hypothalamus, as well as hyperprolactinemia.
The second group covers testicular causes, such as Klinefelter syndrome, which is when they have an extra X chromosome, testicular tumors, crypt orchidism, which occurs when testicles fail to descend into the scrotum, or a varicocele, which is when the veins in the scrotum enlarge and compress the testes.
Pathology6:31–8:24
Finally, the third group covers post-testicular causes, such as tumors and adhesions of the male reproductive ducts, as well as cystic fibrosis, which is a genetic condition that can cause a congenitally absent vasteerens and retrograde ejaculation, which is when sperm is released from the urethra into the bladder instead of outside the body during ejaculation.
Additional causes of infertility in individuals assigned male or female at birth include trauma, infections, and radiation or surgery in the head area, which can impair pituitary production of FSH and LH.
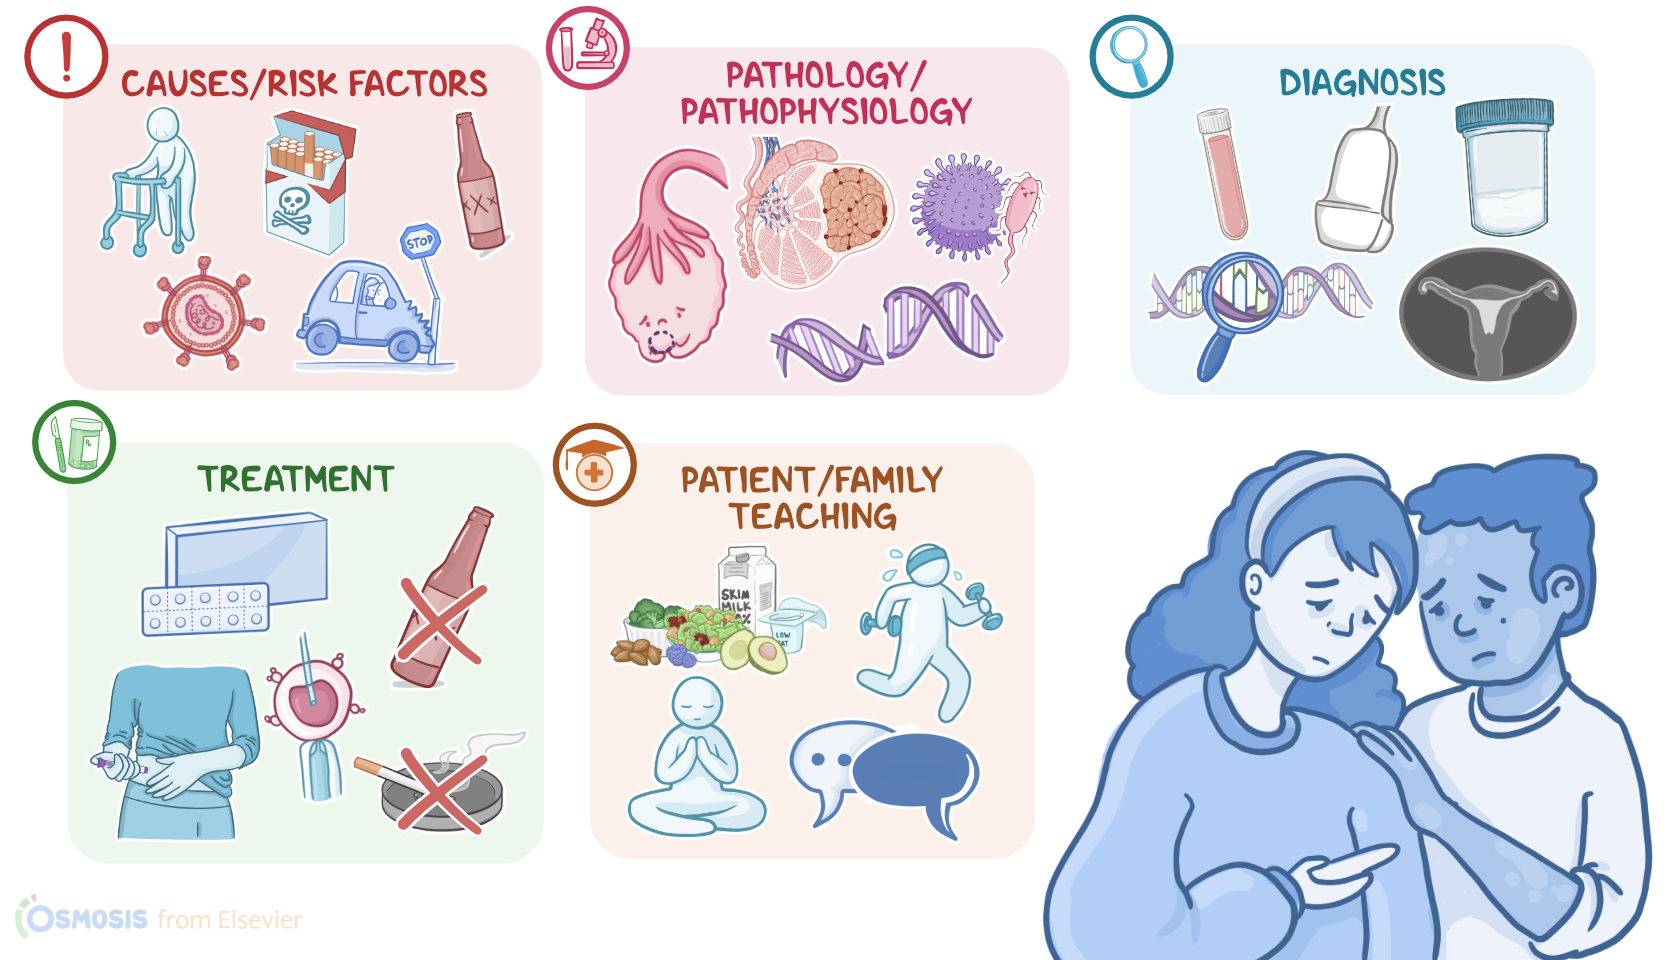
Finally, common risk factors for infertility include advanced age, unhealthy lifestyle habits such as smoking and use of alcohol and drugs, non-malignant chronic conditions like diabetes, sexually transmitted infections, and finally, trauma, infections, and radiation or surgery in the head or reproductive area.
Now let's switch gears and look at the pathology of infertility. In the female reproductive system, there are two types of ovulatory dysfunction, oligoovulation, which is when the ovaries don't release an egg every month.
And anovulation, which is when an egg isn't released at all. Both can be linked with hormone imbalance and damage or abnormalities of the ovary.
With PCOS there's excess testosterone production which can negatively impact oocyte maturation and release. Cushing's syndrome increases cortisol levels, hyperprolactinemia increases prolactin levels, and hyper and hypothyroidism cause abnormal levels of thyroid hormone.
All three can cause dysregulation of FSH and LH secretion. In Coleman syndrome, there's an inadequate production of GNRH from the hypothalamus.
Clinical manifestations8:24–10:35
Leading to decreased release of FSH and LH disrupting the normal ovulation process. Individuals with Turner syndrome typically have small atrophied ovaries.
Next up are adhesions of the fallopian tubes, or inflammation and scarring from pelvic inflammatory disease, which can result in anatomical barriers and disrupt the journey of the fertilized egg into the uterine cavity.
And with endometriosis, endometrial tissue can develop in the fallopian tubes or the ovaries, which either obstructs the passage through the tubes or impairs ovulation, respectively.
Finally, uterine tumors can disrupt the normal anatomy of the uterine cavity, thereby preventing the fertilized egg from attaching to the uterine wall.
Now let's switch our focus to the pathology of the male reproductive system. Pre-testicular causes impair pituitary production of FSH and LH, impairing spermatogenesis.
Testicular problems are associated with poor semen quality and low sperm count. And finally, post-testicular conditions usually result in the obstruction of the ejaculatory system.
Clinical manifestations of infertility depend on the cause, but in individuals assigned female at birth, the most common ones are menstrual disorders, such as irregular menstrual cycles, amenorrhea, or absence of menstruation, dysmenorrhea or extremely painful menstruation, and finally, intermenstrual bleeding, or simply vaginal bleeding at irregular intervals.
Other clinical manifestations can include pelvic masses, which are associated with tumors of the female reproductive system, and galactorrhea, which can be caused by hyperprolactinemia.
Finally, obesity can also be a clinical finding, and individuals with PCOS can present with acne, hirsutism, or excessive hair growth, as well as alopecia or male pattern balding.
Individuals with Turner syndrome typically have a short stature, a broad chest, widely set nipples, as well as broad shoulders and narrow hips, and can also present with congenital skin folds called pterygium coli on the sides of the neck.
Diagnosis10:35–11:14
While those with Coleman syndrome can also have anosmia or an absent sense of smell. On the flip side, individuals assigned male at birth can have testicular masses, suggesting testicular tumors, as well as small testicles or testicles that can't be palpated in the scrotum, suggesting crypt orchidism.
Sometimes secondary sexual characteristics like facial and chest hair can be absent, and gynecomastia, or the presence of breast tissue in those assigned males at birth can be present.
Gynecomastia is a clinical finding that strongly suggests hyperprolactinemia. Additionally, individuals with Klinefelter syndrome typically have a tall stature with long legs, a short torso and broad hips, as well as reduced body hair.
Treatment11:14–11:50
While those with Prader-Villi syndrome typically have excess abdominal fat and stretch marks, a prominent nasal bridge, and absent secondary sexual characteristics.
Lastly, with cranial tumors, individuals can present headaches, visual abnormalities or vomiting, while sexually transmitted infections can cause dysuria, meaning pain or burning when urinating, cloudy urine, and vaginal or penile discharge.
Diagnosis of infertility is based on both clients' history and physical assessment, and is typically followed by blood work, semen analysis, and imaging studies.
Management and care11:50–12:38
Blood work can include measuring levels of LH, FSH, and sex hormones, as well as prolactin, TSH, free thyroid hormones, and cortisol, as well as AMH levels to assess ovarian oocyte reserve.
Additionally, imaging methods can include an ovarian or testicular ultrasound to assess gonad anatomy, or a hysterosalpingogram to assess fallopian tube anatomy.
In some cases, genetic testing can be indicated. Treatment of infertility is based on the cause.
Clients with ovulation problems require pharmacological therapy and the use of fertility medications, while individuals with hormonal imbalances require specific endocrinological treatment.
Finally, clients with tumors or adhesions of the genitourinary tract need surgical treatment. The treatment should be combined with lifestyle changes that include a healthy diet, physical activity, as well as quitting unhealthy habits such as drinking and smoking.
General client and family teaching12:38–13:57
Candidates who still fail to conceive are candidates for assisted reproductive technology such as IVF. OK, when caring for a client with infertility, your priority goals of nursing include assisting them during treatment and providing emotional support.
Most often, you'll be assisting the client during office visits, performing assessments, documenting client information, and assisting with procedures.
You will also spend time assessing your client's understanding about their infertility diagnosis, and their psychosocial status, and talking with them about their feelings and concerns.
Communicate empathy about frustrations and disappointments they are experiencing and provide emotional support. Lastly, acknowledge the many losses they are experiencing throughout the process of diagnosis and treatment.
Be sure to provide referrals for counseling services, as well as information about community resources and local support groups.
Let's move on to client and family teaching. Begin by reviewing the physiology behind their infertility, if it's known, and explain the treatment options that are available to them.
Assist them by answering questions and reinforce the risks and benefits of each treatment option, as well as the estimated rate of success.
Review13:57–16:43
Be sure to provide both verbal and written information. Next, review the lifestyle modifications your client and partner can make to help improve their ability to conceive.
Explain how being either underweight or overweight can reduce fertility, and emphasize the importance of maintaining a healthy weight.
Let them know that moderate exercise will not only help them maintain a healthy weight, it can also help regulate their menstrual cycle.
But to keep in mind that excessive exercise can disrupt the menstrual cycle. Encourage a healthy diet that includes fresh fruits and vegetables, whole grains and protein like seafood, lean meats, legumes, nuts and seeds.
Also work with them to identify stress reduction techniques and coping mechanisms that can support them through the process.
Lastly, stress the importance of practicing safe sex to prevent getting a sexually transmitted infection, which can reduce fertility as well.
Alright, as a quick recap, infertility is defined as the inability to conceive after 12 months of regular unprotected sexual intercourse in couples of reproductive age.
It can affect one or both partners and involves many different factors. Female infertility can be divided into two main groups, ovulatory dysfunction and conditions that affect the normal anatomy of the reproductive system.
Causes of male infertility can be divided into three main groups, pre-testicular causes, testicular causes, and post-testicular causes.
Risk factors for infertility include advanced age, smoking, alcohol and drug use, chronic health conditions, sexually transmitted infections, and trauma, infections, radiation or surgery in the head and reproductive area.
Clinical manifestations of infertility vary depending on the cause, but can include menstrual disorders, pelvic or testicular masses, obesity, and the absence of secondary sexual characteristics.
Diagnosis is based on history and physical assessment, blood work, semen analysis, as well as imaging like ultrasound or a histosalpingogram and genetic testing.
Treatment addresses the underlying cause of infertility and can include fertility medications, specific endocrinological treatment, surgical intervention or assisted reproductive technology.
Nursing management of infertility includes assisting clients during treatment and providing emotional support. Client and family teaching focuses on learning about the factors impacting their condition and lifestyle modifications to help improve their ability to conceive.
| INFERTILITY | ||
| KEY POINTS | NOTES | |
| DEFINITION |
| |
| PHYSIOLOGY |
| |
| CAUSES AND RISK FACTORS |
| |
| PATHOPHYSIOLOGY |
| |
| SIGNS AND SYMPTOMS |
| |
| DIAGNOSIS |
| |
| TREATMENT |
| |
| MANAGEMENT OF CARE |
| |
| PATIENT AND FAMILY TEACHING |
| |
- "Comparison of the effect of Carob capsule and acupuncture on sperm motility, in idiopathic male infertility: A Randomized Controlled Trial. 42:100805. " Journal of Herbal Medicine (2023)
- "Women’s experience of infertility & treatment – A silent grief and failed care and support. 37:100879. " Sexual & Reproductive Healthcare (2023)
- "Seidel’s guide to physical examination (10th ed). ISBN 9780323761833 " Elsevier (2023)
- "Diagnosis and Management of Infertility: A Review. 326(1):65-76. " JAMA (2021)
- "The relationship between the intake of dietary fatty acids and minerals with sperm parameters in infertile men. Clinical Nutrition 58:201-207. " ESPEN. (2023)
- "Harrison’s principles of internal medicine. ISBN 978-1264268504 " Mcgraw Hill (2022)
- "Proven and unproven methods for diagnosis and treatment of infertility. 65(1):93-96. " Adv Med Sci. (2020)
No notes for this video yet
Try adding a note below