Substance use disorder - Medications and illicit drugs: Nursing
Introduction0:00–0:56
. Substance use disorder is a condition that involves cognitive, behavioral, and physiological symptoms that occur when a person continues using a substance, despite significant substance-related problems like missing work or school.
Or impaired relationships with family or friends. Commonly used substances include certain drugs including stimulants like cocaine and methamphetamine, hallucinogens like ketamine and psilocybin, sedative hypnotics like barbiturates and benzodiazepines, opioids such as heroin or morphine, and cannabis.
OK, let's quickly review the physiology of the brain's reward pathway, which governs pleasure and motivation. Inside the brain are molecules called neurotransmitters that are produced and used by neurons to communicate with each other.
Physiology0:56–1:45
This communication happens when one neuron releases a neurotransmitter, which then binds to the receptors of another neuron, causing the neuron to react.
The reward pathway is composed of the mesolimbic system. Which includes the ventral tegmental area in the midbrain, and the nucleus accumbens, a cluster of cells located near the hypothalamus.
The primary neurotransmitter used in this system is dopamine, which causes a feeling of pleasure when released. So when dopamine is released in response to a substance like a sugary treat, for example, a feeling of pleasure occurs.
The dopamine stays in the junction between neurons for a while, until it's taken back into the neuron via dopamine reuptake transporters, and the feeling of pleasure stops.
Causes & risk factors1:45–2:18
Now the prefrontal cortex located in the front of the brain is the area that's responsible for executive functions like decision making and emotional regulation.
It also receives dopamine signals where it evaluates the feelings of pleasure and directs a person's actions like having more of that sugary treat.
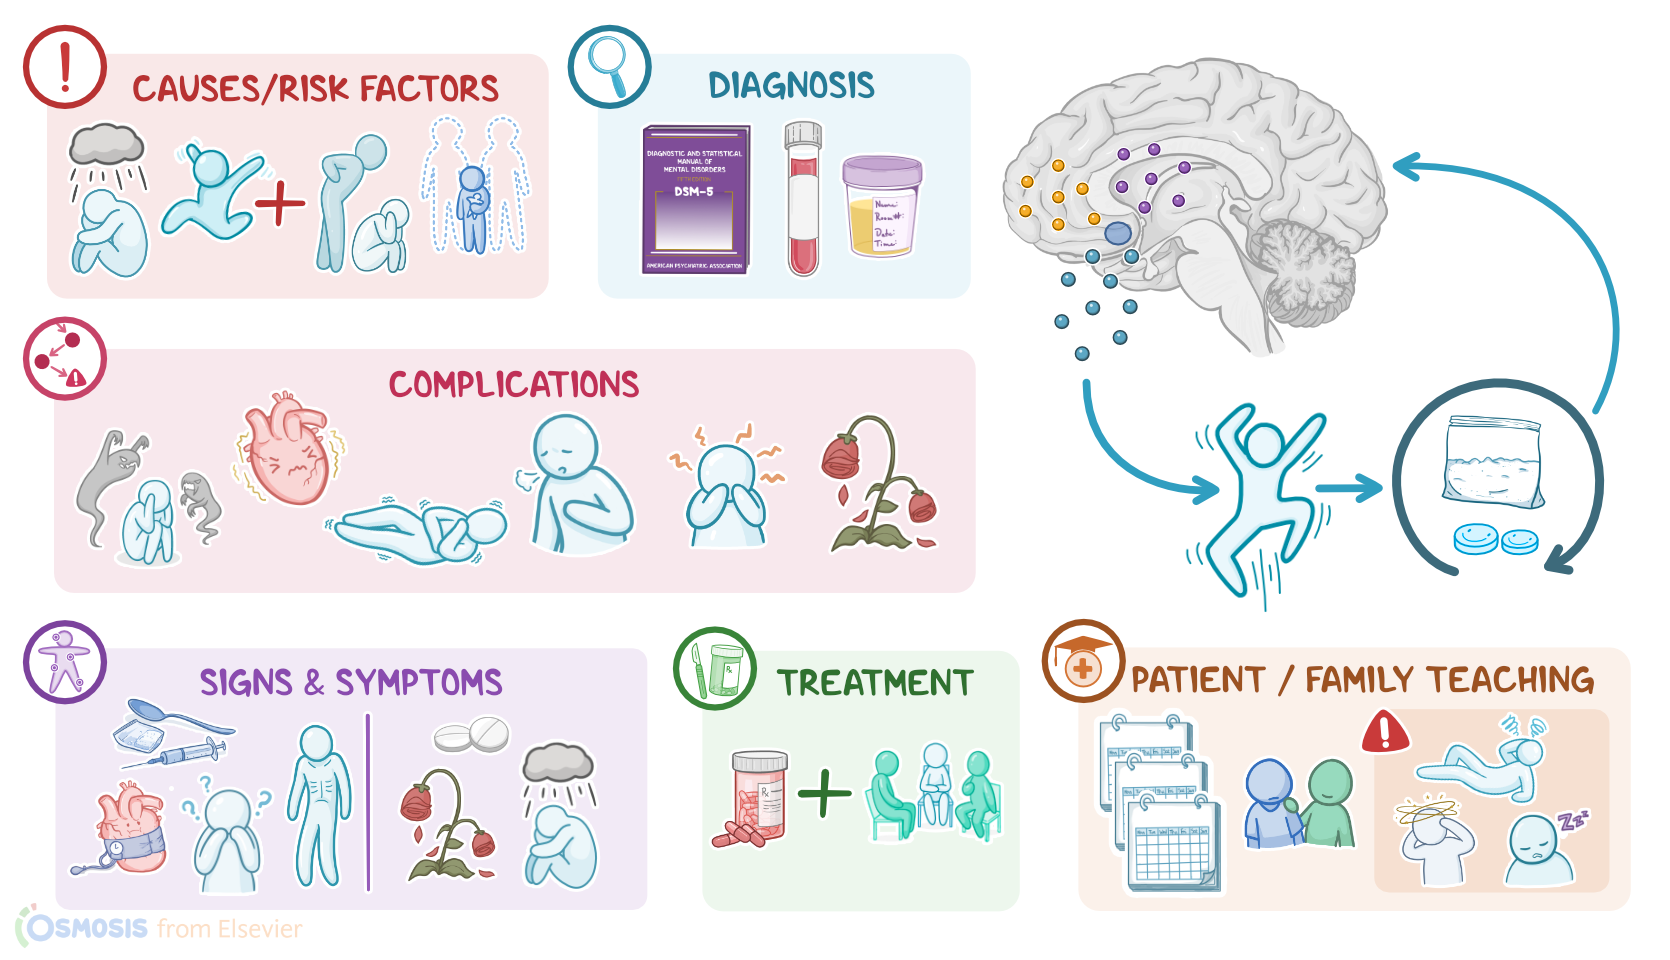
Now, substance use disorders don't have a single cause, but rather the cause is multifactorial, meaning there is a combination of genetic, environmental, social and psychological risk factors involved.
Pathology2:18–5:09
These include a family history of substance use disorder, high levels of family conflict or violence, or having a mental health disorder like depression, ADHD or PTSD.
Certain experiences also put a person at a high risk for developing a substance use disorder, like using the substance at an early age or experiencing abuse or neglect.
Now when considering the pathology of substance use disorder, it's important to keep in mind that not everyone who uses a substance develops substance use disorder.
For example, a single time dose of morphine in the ER for kidney stones will not typically lead to substance use disorder.
However, repeated use of a substance can increase the risk of substance use disorder because it can alter the brain's reward circuitry in ways that lead to strong cravings for the substance.
These cravings can be overwhelming and drive the person to continue to use the substance despite harmful consequences like missing work or school, or damaged relationships with family or friends.
These brain changes also make it hard to stop using the substance, even if the person wants to, and the changes can persist and manifest as relapses, even after successful treatment of substance use disorder.
Now when certain substances are used, it causes an increase in the level of dopamine, either directly or indirectly. For example, cocaine can block the reuptake of dopamine, so it sticks around longer, while some opioids turn off the neurons that inhibit dopamine release, allowing an increased release of dopamine.
These mechanisms extend the euphoric feeling or high, which motivates the person to repeatedly use the substance. Over time, tolerance can develop, which means that with repeated use, a person's euphoric response to the substance decreases.
As a result, a higher dose is needed to achieve the same pleasurable effect as before. At a cellular level, there are two main reasons why this happens.
One reason is that cellular receptors become less sensitive to stimulation by a substance, and the other reason is that the neurons may remove receptors from the cell membrane in a process called down regulation, leaving fewer receptors available for binding.
In either scenario, tolerance leads to more and more of the substance to get the same euphoric feeling. Dependence can also develop, which is the reliance on the substance to function normally.
And if the person stops using the substance, they may suffer from withdrawal symptoms. These symptoms can vary widely from substance to substance.
Diagnosis5:09–6:10
For example, symptoms of opioid withdrawal include sweating and shivering, yawning, abdominal cramps, nausea, vomiting, and diarrhea, while sedative hypnotic withdrawal can manifest as tremors, delirium, and headaches.
These symptoms can feel really awful and often prompt the person to use the substance again. This is called negative reinforcement, since you're removing the substance, which causes withdrawal symptoms, which then reinforces more substance use to avoid those symptoms.
There's also positive reinforcement from the dopamine-induced pleasure and euphoria associated with using the substance, again leading to more substance use.
Together this positive and negative reinforcement leads to substance use disorder. Substances can affect many different areas of the body.
Treatment6:10–8:21
For example, stimulants like methamphetamine and cocaine can increase heart rate, cause vasoconstriction, and increase BP.
This can lead to ischemic damage to the heart, brain, and kidneys. Other effects include paranoia, hallucinations, and dysphoria, as well as a decrease in appetite, leading to weight loss and malnutrition.
On the other hand, opioids and sedative hypnotics can cause central nervous system depression, which could lead to confusion, respiratory and cardiac depression, and even death.
Diagnosis of substance use disorder begins with the patient's history and physical assessment, and is confirmed using the Diagnostic and Statistical Manual for Mental Disorders, 5th edition or DSM-5 criteria, which defines substance use disorder as causing at least two of the following behavior patterns within 1 year.
The substance is taken in larger amount or for a longer period than intended. Being unable to cut down on or control the use of the substance.
Substance use or recovery from use take up a significant amount of time. Having cravings to use the substance.
Having substance use affect responsibilities at work, school, or home. Using the substance even if it causes recurrent interpersonal problems.
Giving up important activities in order to use the substance, using the substance in physically dangerous situations, using the substance even if it's worsening a physical or psychological problem.
Tolerance to the substance unless the tolerance is only under medical supervision and withdrawal symptoms when the substance is stopped.
Having 2 or 3 of these symptoms is considered mild, having 4 or 5 is considered moderate, and having 6 or more is considered severe substance use disorder.
In addition, a blood or urine toxicology test is often performed to identify the substance used. Treatment for substance use disorder usually involves a combination of psychotherapy and pharmacotherapy.
Management of care8:21–9:30
There are several types of psychotherapy that can be helpful, including cognitive behavioral therapy, motivational interviewing, group therapy, and family therapy.
These focus on helping the patient develop strategies to better cope with stress and social pressures, identify the thoughts, feelings and behaviors that lead to substance use, and create a plan to navigate triggers for use.
In addition, patients may benefit from lifestyle modifications like physical activity, yoga, meditation, deep breathing exercises, and acupuncture.
In the case of opioid use disorder, there are several options for pharmacologic treatment, where methadone, naltrexone, or a combination of buprenorphine and naloxone can be given to reduce symptoms and decrease cravings.
Client and family teaching9:30–10:49
OK, let's look at the nursing care you'll provide to a patient experiencing opioid withdrawal. Your primary goal of care is to provide supportive care during withdrawal.
Begin by assessing your patient's airway, breathing, and circulation, or ABC's. For any emergent life-threatening findings, activate emergency protocols as needed.
Then assess your patient's symptoms, which will often reveal tachycardia, elevated BP, elevated body temperature, sweating, and irritability, as well as madriasis or dilated pupils, and pyloerection, which is sometimes called goosebumps.
Once opioid withdrawal is suspected, work with your team to assess the severity of withdrawal using a validated metric such as the clinical opiate withdrawal scale, or COWS for short.
COWS rates common signs and symptoms of opioid withdrawal, including resting pulse rate, pupil size, sweating, restlessness, yawning, bone or joint aches, runny nose or tearing, GI upset.
Review10:49–15:06
Tremor, anxiety, or irritability, and goosebumps. Each sign or symptom is given a number based on severity, and the higher the total score, the higher the severity of withdrawal.
Depending on the severity of withdrawal, be prepared to administer the prescribed buprenorphine or methadone along with adjunctive medications as needed for withdrawal symptoms.
These include alpha 2 adrenergic receptor agonists such as clonidine or lafexidine, which reduce autonomic symptoms. Antiemetics like promethazine, and anti-diarrheals such as loperamide, then continue to monitor your patient closely.
Finally, coordinate ongoing care for your patient, including continued treatment and maintenance. OK, moving on to patient and family teaching.
Begin by explaining that withdrawal from opioids causes both physical and psychological symptoms. Then review the plan of care for an outpatient medication assisted treatment program and explain how the program helps reduce cravings and prevent relapse, some of the risks and benefits of treatment, and the expected length of treatment, which can last months or years.
Then remind them of the importance of keeping all follow-up appointments for counseling to help facilitate a full recovery.
Next, review some strategies to help prevent a relapse. Reassure your patient that relapsing can happen during the recovery process, but it doesn't mean they're failing.
Also encourage them to identify a support person to help them through their treatment program, and be sure to provide them with community resources and support groups for additional support.
Instruct your patient to notify their health care provider if they continue to struggle with abstaining from opioid use and to seek medical attention immediately if they experience signs of an overdose, including slow or shallow breathing, dizziness, drowsiness or difficulty staying awake, fainting or loss of consciousness, as well as if they have any thoughts of harming themselves or others.
Finally, teach your patient's family how to use naloxone in case of an overdose. Alright, as a quick recap, substance use disorder is a condition that involves cognitive, behavioral, and physiological symptoms that occur when an individual continues using a substance despite significant substance-related problems like missing work or school, or impaired relationships with family or friends.
Risk factors include a family history of substance use disorder, high levels of family conflict or violence, having a mental health disorder, and experiencing abuse or neglect.
Substance use disorder starts with an increased level of dopamine, which produces a pleasurable and euphoric feeling. This motivates repeated use of the substance.
Over time, tolerance can develop when the substance has less of an effect, so more and more of the substance needs to be consumed to get the same pleasurable and euphoric feeling.
Dependence develops when the patient needs the substance to function normally. Substance use disorder happens when continued craving for the substance results in compulsive use, despite the harm it causes.
Diagnosis begins with a history and physical assessment and is confirmed using DSM-5 criteria. In addition, blood or urine toxicology tests are often performed to identify the substance used.
Treatment can involve a combination of psychotherapy and pharmacotherapy. The primary goal of nursing care is to provide supportive care during withdrawal.
Patient and family teaching is focused on learning about withdrawal, strategies to prevent relapse, and when to contact the healthcare
| SUBSTANCE USE DISORDER - MEDICATIONS AND ILLICIT DRUGS | ||
| KEY POINTS | NOTES | |
| DEFINITION |
| |
| PHYSIOLOGY |
| |
| CAUSES AND RISK FACTORS |
| |
| PATHOPHYSIOLOGY |
| |
| SIGNS AND SYMPTOMS |
| |
| DIAGNOSIS |
| |
| TREATMENT |
| |
| MANAGEMENT OF CARE |
| |
| PATIENT AND FAMILY TEACHING |
| |
- "Primary care: Interprofessional collaborative practice (7th ed.) ISBN: 978-0-323-93584-5 " Elsevier (2025)
- "Non-pharmacological interventions for methamphetamine use disorder: a systematic review. 212:108060. " Drug Alcohol Depend (2020)
- "Substance Use and Mental Health in Emerging Adult Vs Older Adult Men and Women With Opioid Use Disorder. 29(6):536-542." Am J Addict (2020)
- "Substance use disorders and Medication-Assisted therapies. 58(2):165-181." Nursing Clinics of North America. (2023)
- "CE: Opioid Use Disorder: Pathophysiology, Assessment, and Effective Interventions. 120(6), 38–46." The American journal of nursing (2020)
- "Polygenic Risk for Aggression Predicts Adult Substance Use Disorder Diagnoses via Substance Use Offending in Emerging Adulthood and is Moderated by a Family-Centered Intervention.51(5):607-618." Behav Genet (2021)
- "Assessing Relapse in Patients with Opioid-Use Disorder and Chronic Non-Cancer Pain." Pain Management Nursing ( Published online November 1, 2023)
No notes for this video yet
Try adding a note below